

PGT-A and Genetic Testing Before IVF: What It Is, Who It Helps, and What It Can't Do
If you're preparing for IVF, you've probably encountered the term PGT-A — and a fair amount of confusion around it. Genetic testing of embryos is one of the most talked-about parts of modern fertility care, but it's also one of the most misunderstood, and the evidence about when it actually helps has evolved in recent years.
This guide breaks down what the main types of genetic testing before IVF do, who tends to benefit from each, and — just as importantly — what they can't do. Our goal is to give you an accurate picture so you and your fertility specialist can make the right decision for your situation, rather than a one-size-fits-all decision.
First, a quick distinction: testing embryos vs. testing parents
"Genetic screening before IVF" actually covers two different things that are easy to mix up:
-
Carrier screening tests you and your partner — a blood or saliva test that checks whether you carry genes for inherited conditions you could pass on. It happens before or early in the process and helps identify whether a condition is worth testing embryos for.
-
Preimplantation genetic testing (PGT) tests the embryos themselves, after they're created in the lab, before one is transferred.
This guide focuses on PGT — the testing done on embryos — which comes in three forms: PGT-A, PGT-M, and PGT-SR. If carrier screening raises a specific concern, it often informs which type of PGT (if any) makes sense.
What is PGT-A?
PGT-A stands for preimplantation genetic testing for aneuploidy (formerly called PGS). It examines an embryo's chromosomes to check whether it has the normal number.
A little vocabulary makes the rest of this much clearer. An embryo with the correct number of chromosomes is called euploid; one with a missing or extra chromosome is aneuploid. Aneuploid embryos are a leading cause of failed transfers and early miscarriage, and some aneuploidies lead to conditions such as Down syndrome. PGT-A sorts an embryo batch into euploid, aneuploid, and sometimes mosaic results (more on mosaic embryos below), so your team can prioritize transferring a euploid embryo.
Here's the key idea, and it connects directly to why age matters so much in fertility: PGT-A doesn't change or improve an embryo. It's a sorting tool — it identifies which embryos are chromosomally normal, it doesn't create more of them. As eggs age, a larger share of embryos come out aneuploid, which is why older patients often have fewer euploid embryos to work with. We cover that dynamic in depth in our guide on how age affects fertility.
What PGT-A can do well
For the right patient, PGT-A offers real, specific advantages:
-
It supports transferring a single embryo with confidence. Knowing an embryo is euploid makes it easier to transfer just one, which lowers the risk of twins and the complications that come with multiple pregnancies. ASRM recommends transferring a single euploid embryo regardless of age.
-
It can lower the chance that a given transfer ends in chromosomal miscarriage. By avoiding transfer of aneuploid embryos, it reduces the odds that a particular transfer fails for chromosomal reasons.
-
It can shorten the path for some patients — particularly older patients — by helping avoid transfers of embryos unlikely to succeed.
There's also a reassuring point that links back to age: once a euploid embryo is transferred, live birth rates remain relatively strong across age groups — generally above 50%, with only a slight decline as age rises. Age's biggest effect is on how many euploid embryos you produce, not on whether a euploid embryo, once transferred, can succeed.
What PGT-A can't do — and why it isn't for everyone
This is where the current evidence matters, and where a lot of older online content is out of date. PGT-A is a valuable tool in the right circumstances, but it is not a routine upgrade that benefits every IVF patient.
Leading bodies — including the American Society for Reproductive Medicine (ASRM) — do not recommend PGT-A as a routine test for everyone undergoing IVF. The value of PGT-A as a universal screening test has not been demonstrated, and recent multicenter randomized trials found that overall pregnancy outcomes were similar between IVF with PGT-A and conventional IVF for patients who had blastocysts available to transfer. In other words, for many good-prognosis patients, PGT-A doesn't raise the cumulative chance of having a baby — it mainly changes the order in which embryos are transferred.
Where the benefit is clearest is in specific situations rather than across the board. Research suggests the advantage is concentrated in older patients — one 2024 analysis found cumulative live birth rates improved mainly for patients aged 38 and older — and it can be part of the conversation after recurrent pregnancy loss, though the data there is less definitive.
A few other honest limits:
-
Euploid isn't a guarantee. A chromosomally normal embryo can still fail to implant, and PGT-A doesn't screen for most single-gene conditions (that's PGT-M) or for things like autism.
-
There's a small risk of setting aside a viable embryo. Testing isn't perfect, and some embryos labeled mosaic or abnormal could potentially have led to a healthy pregnancy.
-
It adds cost and time. PGT-A requires a biopsy, lab analysis, and typically a frozen (rather than fresh) transfer.
None of this means PGT-A is a bad choice — for the right patient it's genuinely useful. It means the decision should be individualized, not automatic.
A note on mosaic embryos
PGT-A sometimes returns a mosaic result — an embryo with a mix of normal and abnormal cells. This category has reshaped how specialists think about the test. Mosaic embryos can, in some cases, result in healthy pregnancies, which is part of why discarding embryos on PGT-A results alone can be a mistake. If you have mosaic results, they deserve a careful, individualized conversation with your care team. We explain this in more detail in our introduction to mosaic embryos.
PGT-M: testing for a specific inherited condition
For individuals or couples with a known inherited genetic disorder, PGT-M (preimplantation genetic testing for monogenic disorders, formerly PGD) screens embryos for a specific single-gene mutation — for conditions such as cystic fibrosis, Tay-Sachs disease, or sickle cell anemia. Unlike PGT-A, which counts chromosomes, PGT-M looks for one particular condition the family is known to be at risk of passing on.
Who it's for: families with a known single-gene condition in their history — often identified through carrier screening — who want to reduce the chance of passing it to a child.
PGT-SR: testing for chromosomal structural rearrangements
When one partner has a structural rearrangement of their chromosomes — such as a translocation or inversion — PGT-SR (preimplantation genetic testing for structural rearrangements) helps identify embryos with a balanced chromosomal structure. These rearrangements can contribute to infertility, recurrent pregnancy loss, or genetic conditions, so identifying suitable embryos early can matter a great deal.
Who it's for: individuals or couples known to carry a chromosomal structural rearrangement.
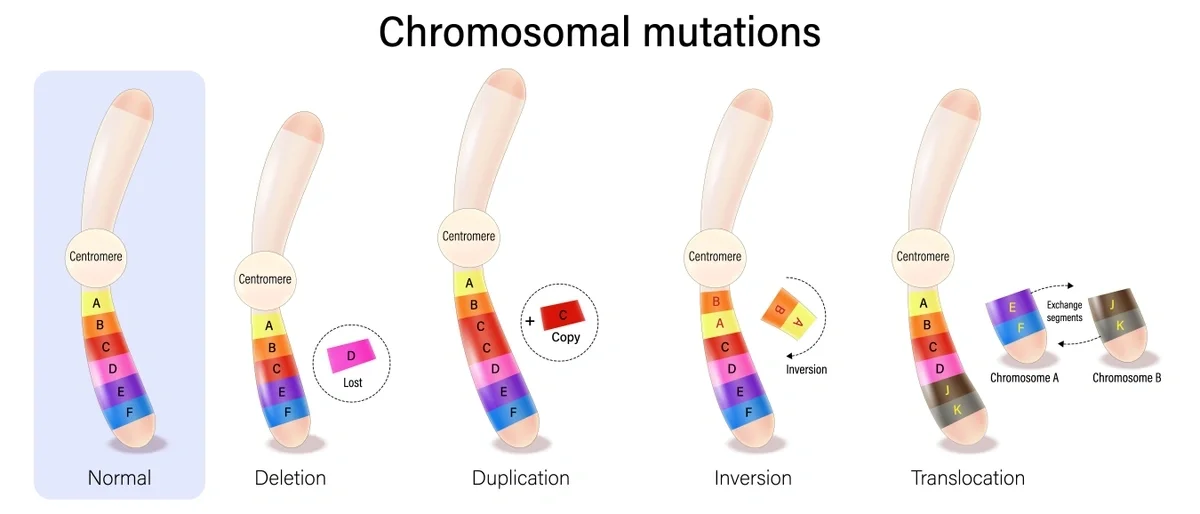
Illustration of different chromosomal mutations
How genetic testing is performed
All three types of PGT follow the same basic process. After eggs are retrieved and fertilized, embryos are grown to the blastocyst stage (around day 5–7). A small number of cells are then biopsied from the part of the embryo that will become the placenta and sent to a specialized lab for analysis. The biopsy is performed by experienced embryologists and is generally considered low-risk when done at this stage. Because results take time, embryos are frozen while you wait, and a euploid (or suitable) embryo is transferred in a later cycle — one reason PGT usually goes hand in hand with a frozen embryo transfer (FET).
Embryo grading and genetic testing answer different questions, by the way — grading assesses an embryo's appearance and development, while PGT assesses its chromosomes. Many patients weigh both together, which we cover in our guide to embryo grading.
Is genetic testing right for you?
There's no universal answer, but these are the factors worth discussing with your specialist:
-
Age. Because aneuploidy rises with age, PGT-A's potential benefit is greatest for older patients.
-
A known genetic condition or chromosomal rearrangement. This is where PGT-M or PGT-SR can be specifically valuable.
-
A history of recurrent pregnancy loss. PGT-A may be part of the discussion, though it isn't a guaranteed solution.
-
Your priorities and values. Some patients want every available data point; others prefer to limit testing, cost, or the number of embryos set aside. All are valid.
The right decision balances the clinical evidence for your specific situation with what matters most to you — which is exactly the kind of conversation your fertility team is there to have.
Frequently asked questions
What is PGT-A? PGT-A (preimplantation genetic testing for aneuploidy) is a test performed on IVF embryos to check whether they have the normal number of chromosomes. It identifies which embryos are euploid (normal) so a chromosomally normal embryo can be prioritized for transfer.
Does PGT-A improve IVF success rates? It depends on the patient. PGT-A helps identify a euploid embryo and supports transferring one at a time, and it can reduce the chance a given transfer ends in chromosomal miscarriage. But recent large trials found it doesn't raise the overall chance of a live birth for many good-prognosis patients, and ASRM doesn’t recommend it as a routine test for everyone. Its benefit is clearest for older patients.
What's the difference between PGT-A, PGT-M, and PGT-SR? PGT-A counts chromosomes to find embryos with the normal number. PGT-M tests for a specific single-gene condition a family is known to carry. PGT-SR checks for balanced chromosomes in people with a known structural rearrangement.
Is a euploid embryo guaranteed to become a healthy baby? No. A euploid embryo has a strong chance of implanting, but it's not a guarantee, and PGT-A doesn't screen for most single-gene conditions or every health outcome.
What is a mosaic embryo? A mosaic embryo has a mix of chromosomally normal and abnormal cells. Some mosaic embryos can result in healthy pregnancies, so mosaic results call for an individualized discussion with your care team rather than an automatic decision.
The Bottom Line
Genetic testing before IVF is a powerful tool — when it's matched to the right situation. PGT-A can help the right patients transfer a single embryo with confidence and avoid transfers unlikely to succeed, while PGT-M and PGT-SR serve families with specific known risks. What testing can't do is guarantee a pregnancy or benefit every patient equally, which is why the current guidance emphasizes an individualized decision over a routine one.
At Tennessee Fertility Institute, we'll help you weigh whether — and which — genetic testing fits your treatment plan, your history, and your goals. Request a consultation to talk it through with a specialist.